

In 1930, the economist John Maynard Keynes made two bold predictions. The first was that the global economy would grow roughly eightfold by the early 21st century. That one proved remarkably accurate. The second was that this prosperity would free us from long working hours, leaving most of us working only about 15 hours a week. On the second prediction, Keynes missed badly.
Most of us are working just as hard as ever. And the reason he got it wrong has profound implications—for your financial independence and for the chronic disease epidemic you are managing in your clinic every day.
What Keynes failed to anticipate was a phenomenon social scientists call social comparison or what most people know simply as “keeping up with the Joneses.” The size of the average American home, for example, has more than doubled since the time of his writing, packed with more “stuff” than ever before. Rather than converting economic growth into free time, we converted it into consumption. And instead of gaining independence from our employers, the large majority of us remain financially tethered to our jobs to fund a growing list of expenses, many of which we didn’t know we needed until our neighbors got them first.
As physicians, most of us know what financial dependence feels like professionally: staying in a job or a system because we need the income, not because we love the work. What we may not have fully considered is how that same dynamic, operating at a societal scale, is one of the primary drivers of the chronic disease epidemic we are fighting every day in clinic.
That is the argument I want to make.
Mindless Consumerism and the Rise of Chronic Disease
Homo sapiens have been on Earth for roughly 300,000 years. The post-industrial era we currently live in represents just 0.1% of that time. For over 95% of human history, we were hunter-gatherers.
In 2016, researchers from Oregon State University measured how many American adults were living healthy lifestyles across four criteria: regular physical activity, a healthy diet, a normal body fat percentage, and not smoking. The result was that only 2.7% of participants met all four.
That is a stunning failure. But before concluding that the problem lies with human nature itself, it is worth considering some historical context. How would our Paleolithic ancestors have fared on those same four metrics?
- Physical activity: Hunter-gatherers spent their days hunting, foraging, and moving constantly, engaging in at least 10 times more daily moderate-to-vigorous physical activity than modern recommendations require.
- Diet: When food was available, it was natural, whole, and nutrient-dense. They simply didn’t have the option of ordering the family bucket at the local KFC drive-through.
- Body fat: Studies of contemporary hunter-gatherer populations, such as the Hadza in Tanzania or the Tsimané in Bolivia, show consistently leaner body compositions even when food is plentiful, driven by diet quality and activity rather than any deliberate restriction.
Smoking: This was virtually nonexistent until very late in the Paleolithic era.
We can conclude that when food was sufficiently available, our ancestors easily passed this test. Today, we have largely solved food insecurity. Why, then, do we collectively fail so miserably?
More information here:- Merging Financial Responsibility and Environmental Sustainability
- Would You Encourage Your Child to Be a Doctor?
The Scale of the Problem
Before answering that question, consider the consequences of this collective failure.
Worldwide adult obesity has more than doubled since 1990. Adolescent obesity has quadrupled over the same period. Obesity rates are increasing in every country without exception. Diseases that were rare or essentially nonexistent among hunter-gatherers are now commonplace (see the table below). In the United States, 90% of the nation’s $5.3 trillion in annual healthcare expenditures go toward people with chronic health conditions.
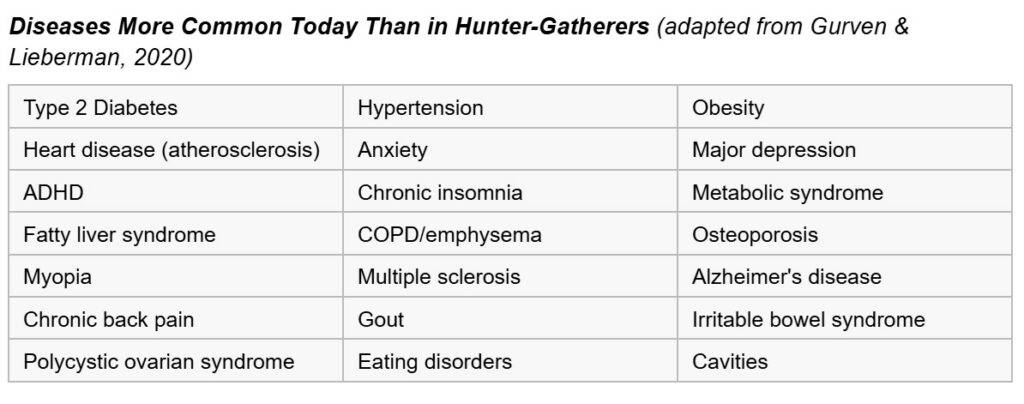
A common objection is that our ancestors didn’t live long enough to develop these diseases. But this doesn’t hold up. Research on contemporary hunter-gatherer populations—including elderly members who regularly reach their 60s and 70s—reveals minimal chronic cardiovascular disease, obesity, or diabetes. They have markedly healthier body compositions than modern populations of the same age. Lifestyle factors, not merely longevity, are driving these trends.
3 Ways Consumerism Drives Chronic Disease
This is where Keynes becomes relevant again. If consumerism keeps us financially dependent and if financial dependence keeps us working long hours in whatever job is available (not necessarily the one we’d choose if money weren’t the primary concern), then consumerism makes healthy living more challenging. Here are the problems.
#1 Modern Employment Is a Health Hazard
Over 80% of US workers are largely sedentary on the job. Similar trends are emerging globally. Given the pace of modern work life, many people start the day with quick, highly processed food options and end it understandably too tired to prepare a nourishing meal for themselves and their families. Over decades, this compounds directly into chronic disease.
The connection to consumerism is precisely what Keynes didn’t foresee. Economic growth did not translate into leisure. It translated into bigger homes, more possessions, and a higher baseline cost of living that keeps us tethered to demanding jobs. Overconsumption, in essence, is what locks us into the working conditions that are making us sick.
#2 We’ve Engineered Ourselves Out of Our Natural Environment
Consumerism has transformed our physical environments from natural to increasingly artificial. But we evolved in natural environments. Americans now spend well over 90% of their time indoors. Our Paleolithic ancestors spent 100% of their time outside.
The lack of exposure to natural light, fresh air, and green spaces is associated with a range of adverse health outcomes. It is not difficult to see why anxiety, depression, and other mental health disorders are rising alongside every other chronic condition.
Consider the modern garage. It requires a driveway, which requires a paved road built to every household. We have effectively engineered out the need to use our legs in a meaningful way. Children travel from home to school by bus or car. Adults drive to work. The result is that generations of people reach the end of each day having spent almost no time outdoors and having used their bodies for almost nothing.
#3 Financial Dependence Determines Which Industries Survive
This is the argument I find most underappreciated.
A person who is financially independent works for a fundamentally different reason than one who depends on their employer for income. Financial independence, or the ability to stop working without ever running out of money, means you work primarily because you are passionate about the product or service. Money is a desirable side effect. In contrast, a person who is financially dependent on their employer (the vast majority) has to work for money, and the product or service is the side effect.
At a societal scale, the implications are significant.
Consider food. Between 60%-70% of the US food supply has been re-engineered to maximize addiction and consumption, often at the direct expense of the health of its customers. McDonald’s employs hundreds of thousands of people. Hypothetically, if half of those employees were financially independent, a significant proportion would leave for more meaningful work. McDonald’s would shrink in size and sell less harm to the public. That outcome, regardless of what we’ve been taught is good for the economy, is good for the people.
Consider tobacco. Philip Morris sold cigarettes while knowingly misrepresenting the health risks, suppressing research for years and marketing to children to establish addiction early. Beyond the executives, their workforce consisted of ordinary, hardworking people who were simply trying to earn a living. They were not passionate about cigarettes, but they were financially dependent on the income. Without those workers, companies like Philip Morris could not have operated at scale. Financial independence among even a fraction of that workforce would have hollowed them out from within.
The larger point is that financial independence fundamentally realigns the incentive structure of work. People who are financially free choose work that is meaningful to them. And meaningful work, at scale, tends to look very different from the industries currently causing the most harm to human health.
More information here:- Lessons Learned from Achieving Financial Independence
- Beyond Financial Independence: Money Irrelevancy
- Life After Financial Independence: Two Perspectives
Has All This Consumption Made Us Happier?
What if all this consumption—the larger homes, the better cars, and the abundance of things our grandparents never imagined—has made us happier? Wouldn’t that justify some of the tradeoffs?
According to the 2018 World Happiness Report, despite dramatic increases in GDP per capita over recent decades, average happiness has slightly declined. One of the contributing factors cited is the rise in chronic disease discussed above. In other words, all this spending is increasing chronic disease, and chronic disease is decreasing happiness.
What does the research show increases happiness? The list is fairly consistent across studies: physical activity, nutritious food, good sleep, a sense of security, a sense of purpose, time with family and friends, and a sense of agency over one’s own life.
Notice what these things have in common. Apart from food and security, they are free. In other words, once your basic needs are met, the best things in life are free.
The Prescription
If mindless consumerism is a primary driver of the chronic disease epidemic, then the prescription follows directly. You should consume mindfully.
No, this is not a call to return to Paleolithic life. Modern medicine, vaccines, clean water, and an abundant food supply are genuine achievements. But my argument is that we can take the genuine benefits of modernity without accepting the chronic disease burden that comes with unchecked overconsumption.
For physicians treating patients, there is a reframe worth considering. Telling patients to eat better and exercise more has not moved the needle at a population level. Today, we have decades of evidence for that. The environment people live and work in and the financial pressures they operate under determine behavior far more than any individual health campaign. Addressing those upstream determinants, including the financial structures that keep people locked into unhealthy patterns of work and consumption, may be the more honest and more effective conversation.
For physicians pursuing financial independence, the implications are both personal and larger than they might initially seem. The financially independent physician who leaves a soul-draining position, who advocates openly for better care without worrying about institutional politics, or who structures their work life around what is actually meaningful is also, in a small way, modeling a different relationship between work, consumption, and wellbeing.
We do not need to be ultra-wealthy to reach financial independence. What we need is to stop normalizing standards of living built on things we don’t actually need (the oversized homes, the status cars, the endless gadgets) and recognize that once basic needs are met, the factors that genuinely drive health and happiness are largely free. That message is at the heart of both the FIRE movement and, it turns out, the solution to the chronic disease epidemic.
Do you feel your life is fueled by consumerism? If so, how does that affect your happiness? What could you do to change that?
Did you find this article helpful? Share it!



